
Innovation Before Disease: The Next Frontier in Metabolic Health
At the 2026 World Medical Innovation Forum, leaders from medicine, food innovation, and investment explored a provocative proposition: What if preventing metabolic disease became a viable business model rather than an elusive public health aspiration?
For decades, modern healthcare has excelled at treating disease while struggling to prevent it. We have developed extraordinary technologies, powerful pharmaceuticals, and increasingly sophisticated medical interventions. Yet chronic metabolic diseases continue to overwhelm healthcare systems, consume national budgets, and diminish the quality of millions of lives.
What if the next great medical innovation isn’t another treatment, but a fundamental redesign of the conditions that make us sick?
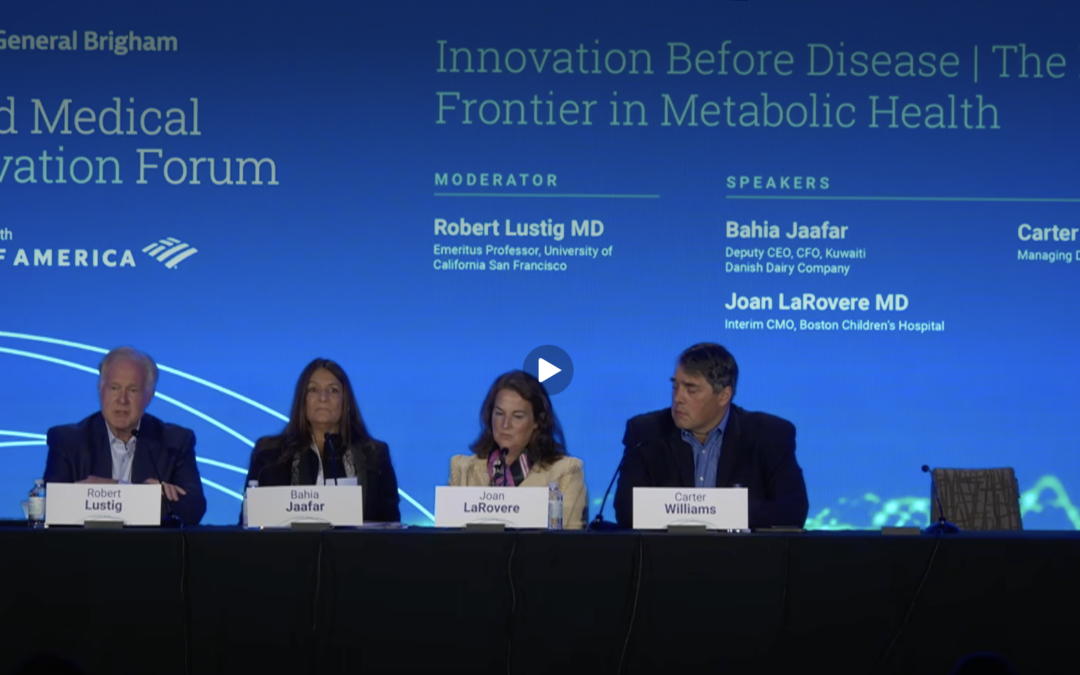
That question animated a compelling discussion at the 2026 World Medical Innovation Forum, hosted by Mass General Brigham, where Dr. Robert Lustig, Professor Emeritus at the University of California, San Francisco, moderated a panel featuring Bahia Jaafar, Deputy CEO and CFO of the Kuwaiti Danish Dairy Company (KDD); Dr. Joan LaRovere, Interim Chief Medical Officer at Boston Children’s Hospital; and Carter Williams, Managing Director of iSelect Fund.
Their perspectives converged on a powerful idea: Prevention must become scientifically measurable, commercially viable, and scalable across entire populations.
The Economics of Waiting for Disease
Dr. Lustig opened with an anecdote that captured the problem. A publisher had reportedly rejected his latest book because its market research suggested that books containing the word prevention simply don’t sell.
The irony is difficult to ignore. Prevention may be commercially unpopular, but the consequences of failing to prevent disease are extraordinarily expensive.
Lustig described how nine major chronic conditions account for an estimated 75 percent of American healthcare spending. Despite remarkable advances in treatment, these conditions remain largely chronic, requiring ongoing management rather than offering definitive cures.
He also challenged the notion that the emergence of GLP-1 medications represents a complete solution. While acknowledging their therapeutic value, he argued that widespread pharmaceutical intervention cannot substitute for addressing the underlying drivers of metabolic dysfunction.
At the heart of his argument was mitochondrial health. Mitochondria, the cellular structures responsible for energy metabolism, play a central role in metabolic function. Lustig emphasized that what we eat directly influences these processes, making food a critical intervention point long before disease manifests clinically.
His economic framing was equally provocative: the financial rewards associated with producing unhealthy foods are accompanied by enormous downstream costs borne by healthcare systems, governments, employers, and society.
The opportunity, he argued, is to redirect economic value toward preventing those costs in the first place.
From Treating Disease to Designing Health
Dr. Joan LaRovere offered a healthcare system perspective, explaining that modern medicine was largely built around acute care: diagnosing illness, rescuing patients, and treating established disease.
These systems perform extraordinarily well when someone needs emergency surgery or intensive care. But they were never designed to address the gradual development of metabolic dysfunction over decades.
LaRovere argued that meaningful prevention must begin much earlier, particularly in childhood, when many of the biological and behavioral trajectories associated with adult disease are established.
She also identified a promising opportunity in artificial intelligence and longitudinal pediatric health records. Decades of screening have generated extensive data that could help identify metabolic risk long before conventional diagnostic thresholds are reached.
The implications are profound. Rather than waiting for a diagnosis of type 2 diabetes or cardiovascular disease, healthcare systems could potentially recognize early warning signals and intervene when changes in diet, lifestyle, and environment are most likely to make a difference.
Lustig pushed the timeline earlier still, emphasizing that metabolic health begins before birth, with maternal nutrition and metabolic conditions influencing the health trajectories of future generations.
Prevention, in this framing, is not simply a healthcare intervention. It is a lifelong—and even intergenerational—design challenge.
Can the Food Industry Become Part of the Solution?
Perhaps the most tangible example of prevention moving from theory into commercial practice came from Bahia Jaafar, Deputy CEO and CFO of KDD.
Based in Kuwait, a country facing exceptionally high rates of obesity and diabetes, KDD began asking a fundamental question in 2020: Could a mainstream food and beverage company redesign its products to deliver positive metabolic health outcomes without sacrificing taste, affordability, or commercial viability?
Working with an international team of scientists, the company developed the Metabolic Matrix, an evidence-based food design framework organized around three interconnected principles:
- Feed the Gut — support microbiome health and function.
- Protect the Liver — reduce metabolic stress and support healthy liver function.
- Support the Brain — promote neurological and metabolic well-being.
Rather than treating health as a marketing claim or relying exclusively on nutrient fortification, the framework examines how ingredients, processing methods, and finished products influence human metabolism.
Jaafar described how KDD translated this science into its GOOD FOR ME product platform, beginning with a reformulated chocolate ice cream.
The choice was deliberate. Instead of asking consumers to abandon foods they enjoy, KDD sought to demonstrate that familiar indulgences could be redesigned with metabolic health in mind.
Developed with support from the Kuwait Foundation for the Advancement of Science, the ice cream underwent a nine-month evaluation with the Dasman Diabetes Institute. Jaafar reported encouraging insulin-related findings among participating patients, providing an early example of how food innovation could be connected to clinical investigation.
The GOOD FOR ME range has subsequently expanded into beverages, dairy products, and additional frozen desserts, including products without added sugar.
Most importantly, Jaafar reported that the platform has become profitable.
That commercial milestone matters. It challenges the assumption that metabolically healthier food must remain a niche, subsidized, or philanthropic proposition.
If food can be redesigned to support better metabolic health while remaining desirable and commercially sustainable, prevention becomes an opportunity for mainstream industry rather than a responsibility assigned exclusively to healthcare.
Making Prevention Investable
Carter Williams brought the investor’s perspective, arguing that successful innovation often occurs when a better solution also becomes economically more attractive than the alternative.
The challenge is therefore not simply to persuade consumers to make healthier decisions. It is to redesign markets so that healthier choices become accessible, convenient, desirable, and ultimately more affordable.
Williams encouraged the audience to imagine an economy without the enormous burden of chronic disease—and then work backward to identify the investments and innovations needed to approach that future.
For insurers, employers, pension funds, and governments, the potential returns extend well beyond reduced medical expenditures. A metabolically healthier population could mean greater productivity, longer healthy working lives, reduced disability, and improved quality of life.
But realizing those returns requires new business models and better ways of measuring prevention’s economic value.
It also requires recognizing that the organizations paying for prevention are not always the same organizations that capture the financial benefits.
Closing that gap could unlock substantial investment in food innovation, early detection, and healthier environments.
A New Frontier for Healthcare Innovation
What made this World Medical Innovation Forum discussion particularly important was the convergence of perspectives.
A physician-scientist described the biological mechanisms of metabolic dysfunction. A pediatric healthcare leader explained where prevention could begin. A food industry executive demonstrated how metabolic science could influence commercial product development. And an investor articulated how prevention might attract capital at scale.
Together, they pointed toward a different model of healthcare innovation—one in which the food industry, agriculture, healthcare providers, researchers, insurers, and investors share responsibility for creating the conditions that support metabolic health.
The implications reach far beyond any individual product, therapy, or institution.
They suggest that one of the most consequential opportunities in healthcare may lie outside the traditional healthcare system itself: in the everyday foods billions of people consume.
For the Metabolic Matrix initiative, the discussion reinforced a central conviction that has guided its development: Food should be designed not merely to avoid harm, but to actively support metabolic health.
The next frontier is translating that ambition into measurable health outcomes, viable commercial models, and population-scale implementation.
As Dr. Lustig has repeatedly emphasized:
“Prevention is the cure.”
The challenge now is to make prevention work—not only biologically, but economically, commercially, and at the scale the global metabolic health crisis demands.
Watch the Discussion
Innovation Before Disease | The Next Frontier in Metabolic Health
World Medical Innovation Forum 2026 | Mass General Brigham
Watch the full panel discussion on YouTube
Panelists: Dr. Robert Lustig (Moderator), Bahia Jaafar, Dr. Joan LaRovere, and Carter Williams.
Further exploration: The Metabolic Matrix | Metabolica